Five years after spinal fusion, the leg pain that once kept you awake has returned. You can still walk, but standing at the kitchen counter brings on a deep ache. Your first thought may be that the operation failed. Another possibility is adjacent segment disease, which can affect a disc or joint next to the fused part of your spine.
A scan may show wear even when a person feels well. Your symptoms and exam guide the next step.
What Adjacent Segment Disease Means After Fusion
During spinal fusion surgery, a surgeon joins two or more vertebrae so they heal into one stable unit. Those bones no longer move as separate joints. Nearby discs still bend.
Adjacent segment degeneration refers to wear seen on imaging near a prior fusion. Adjacent segment disease means the nearby changes have begun to cause symptoms, such as nerve pain or trouble walking. Some disc changes never cause pain or need treatment.
Why Nearby Spinal Levels Can Wear Down
Think of the spine as a row of connected joints. When one section no longer bends, the joints beside it take on more movement. That added load may increase disc wear. Age also plays a role. Discs lose water and height with age. This wear can occur without surgery.
How Spinal Alignment Affects Nearby Discs
Your lower-back curve helps spread weight across the pelvis and spine. Surgeons compare the curve of the lumbar spine with the position of the pelvis. If those angles do not match well, the nearby discs can face added strain when a person stands upright.
A 2026 review in the Journal of the American Academy of Orthopaedic Surgeons identified weight, existing disc wear, and poor spinal alignment as risk factors. Doctors also assess nearby discs before a cervical spinal fusion, although neck and lower-back surgery use different measures.
Adjacent Segment Disease Symptoms That Need a Check
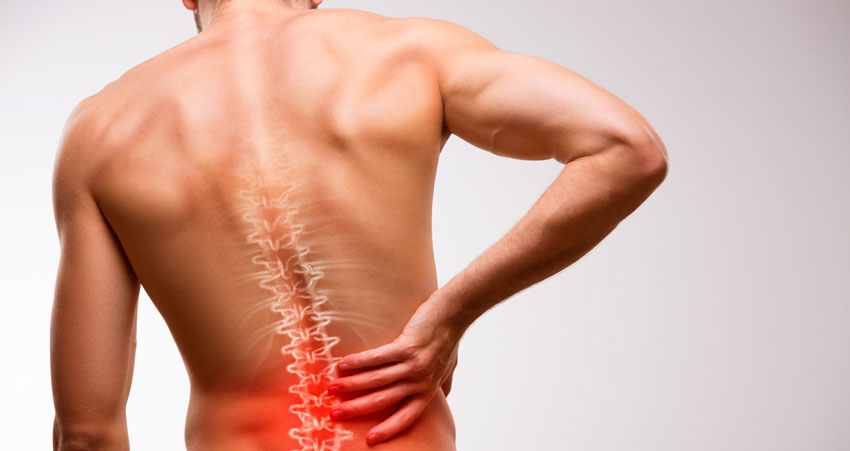
In the lower back, a new pinched nerve may cause pain that travels into one leg. Tingling, numbness, and reduced foot strength can also occur. Some people feel better when they sit or lean forward, especially if the spinal canal has become narrow.
After neck fusion, new hand weakness or poor balance can point to pressure on the spinal cord. Call your surgeon promptly if these problems appear. Seek emergency care for new loss of bladder or bowel control, numbness around the groin, or rapidly worsening leg weakness. These signs can be linked to severe nerve compression. Mention any recent injury, fever, or unexplained illness when you seek care, since other causes of back pain may need urgent treatment.
What 2026 Research Found About Adjacent Segment Disease
A 2026 study in World Neurosurgery looked back at 419 patients who had surgery to fuse one or two levels of the lower back. Of those patients, 259 had open surgery and 160 had a minimally invasive approach. Researchers tracked later operations for adjacent segment disease, along with other health outcomes.
In the open group, 19% had another operation for the condition, compared with 9% in the minimally invasive group. These figures describe the patients in the study. They do not predict an individual patient’s risk.
With minimally invasive spinal surgery, surgeons may reach the spine through smaller openings and limit injury to some nearby tissues. Researchers suspect less harm to nearby facet joints could explain part of the result.
Why the Two Surgery Groups Need Careful Comparison
The study used past medical records. Patients were not assigned at random. Their health and the reasons for surgery may have differed. There is another limit that can be easy to miss: the study counted repeat operations. It did not include every case of disc wear or new pain. Average follow-up was under three years.
Can You Reduce the Risk of Adjacent Segment Disease?
Before fusion, surgeons review the levels that need treatment and check the discs beside them. They also assess spinal balance. Careful planning may reduce avoidable strain, although no approach can promise that nearby discs will stay healthy for life.
After surgery, follow the activity limits and rehab plan given by your care team. Walking and guided exercise can help rebuild strength once the surgeon says they are safe. If you smoke, ask for help quitting. These steps support healing but cannot prevent every case.
Why the Number of Fused Levels Deserves Attention
Surgeons try to treat the levels that cause the problem. A shorter fusion may leave an unstable level untreated, so the number of levels needs careful planning. Before surgery, ask which levels need fusion and what the images show at the levels next to them.
How Doctors Diagnose Adjacent Segment Disease
Your doctor may begin by asking where the pain travels, when it began, and what brings it on. An exam can check strength, reflexes, and feeling in the arms or legs. Bring the date of your first surgery and any earlier scans to the visit, if you have them. MRI can show pressure on nerves and changes in the discs. CT helps doctors assess bone, screws, and the fusion itself. Standing X-rays may reveal changes in spinal alignment. Your team may compare them with scans taken before the first operation.
Not every new ache comes from an adjacent disc. Pain may arise from the hip, sacroiliac joint, muscles, or the original fusion. Matching the exam to the scans helps the care team decide where treatment should begin.
Treatment Choices Before Another Operation
For pain without severe or worsening nerve loss, treatment may start with physical therapy or medicines. Some people may benefit from a targeted injection.
Some people need another operation when nerve pressure causes major limits or weakness, or when the spine has become unstable. A surgeon may relieve nerve pressure or extend the fusion. During revision spine surgery, scar tissue and existing hardware can make planning more complex.
Before agreeing to surgery, ask which finding explains your symptoms, which treatment choices remain, and what improvement is realistic. Your answers will depend on the exam and any signs of nerve damage.
Common Questions About Pain After Spinal Fusion
How do I describe new pain to my surgeon?
Write down where the pain starts, where it travels, and whether sitting or walking changes it. Note any numbness or weakness and when it first appeared. Bring that record to the appointment so the doctor can compare your symptoms with the images.
What if my MRI shows disc wear but I have no pain?
Your doctor may call that adjacent segment degeneration. It may need no treatment if the finding causes no symptoms. Ask your doctor whether the scan shows nerve pressure and whether the finding matches your exam. Imaging alone cannot tell you whether treatment will help.
Should I get a second opinion before another fusion?
A second opinion can help when the proposed surgery is complex or the cause of pain is uncertain. Bring the report from your first operation, recent images, and a list of treatments you have tried. Ask each surgeon which spinal level is causing the symptoms and why the planned procedure addresses it.
What to Bring to Your Next Spine Appointment
Start with your prior operation report, the dates of your new symptoms, and copies of recent scans. Include a short record of how far you can walk and which tasks bring on pain. The 2026 studies give doctors better questions to explore, but your exam and imaging remain the basis for a treatment plan. If you develop new weakness or other warning signs, seek care without waiting for a routine visit.